 ·

OMA Insurance Review for Ontario Doctors: Keep, Layer or Replace?
By Parvesh Benning, Licensed Life Insurance Broker
The real question is not OMA versus private. It is which parts of your OMA coverage to keep, which to layer over, and which to replace.
A good broker will not tell you to cancel OMA the moment you walk in. OMA coverage is real, and some of it is worth keeping. This page is a contract-based review of what your OMA life, disability, and critical illness coverage actually does, where it falls short for a higher-earning or incorporated physician, and where private coverage earns its place.
Updated: October 7, 2026

OMA Insurance Review for Ontario Doctors: Keep, Layer or Replace?
By Parvesh Benning, Licensed Life Insurance Broker, Updated: October 7, 2026
The real question is not OMA versus private. It is which parts of your OMA coverage to keep, which to layer over, and which to replace.
A good broker will not tell you to cancel OMA the moment you walk in. OMA coverage is real, and some of it is worth keeping. This page is a contract-based review of what your OMA life, disability, and critical illness coverage actually does, where it falls short for a higher-earning or incorporated physician, and where private coverage earns its place.
Most physicians treat OMA Insurance as all or nothing: keep the whole package, or cancel it and start over. That framing is wrong, and it is usually what leads to a bad decision in either direction.
OMA gives you genuine coverage through your association: group life, disability, and critical illness, plus the subsidized OPIP program. For a resident or a new physician, it is often a sensible starting layer. The gaps tend to show up later, as your income climbs, once you incorporate, or when you need contract guarantees a group plan cannot offer. The job is to work out which OMA pieces still pull their weight, which ones to layer private coverage over, and which ones to replace outright.
This guide walks through OMA’s life, disability, and critical illness coverage as it stands today, then covers two areas almost no comparison touches: owning insurance inside a medical professional corporation, and using a policy as collateral for a practice loan. If you are incorporated, those last two are often where the planning value matters most.
Who this is for
Ontario physicians, residents, and incorporated doctors who already have OMA coverage and want to know what to keep, what to add, and what to change, before touching anything.
What a proper review checks
- What your OMA life, disability, and critical illness actually cover, and where they stop
- Whether your disability definition protects your specialty, or only protects you while you cannot work at all
- What changes once you incorporate, and whether your policy should be owned by your medical corporation
- Whether a policy can be used as security for a practice loan
- What not to cancel until replacement coverage is approved and in force
One rule before anything else: do not cancel existing coverage until new coverage is approved, issued, and reviewed.
OMA vs Private Coverage for Physicians: At a Glance
The short version, before the detail: this is rarely all or nothing. Here is where physicians tend to keep OMA, and where individually owned coverage usually earns a look.
Every row below gets the full treatment, including what OMA actually covers today, where the gaps show up, and what individually owned coverage costs. If you would rather have a broker read your certificate before deciding anything, that review is free, and how to book it is at the bottom of this page.
What this review covers
- What OMA Insurance actually includes
- OMA life insurance: Term Life Plus 75 and Flex Term
- OMA disability insurance: what it covers, and the gaps that matter
- OMA critical illness and OPIP critical illness
- Owning insurance through your medical professional corporation
- Using life insurance as collateral for a practice loan
- When OMA fits, when private fits, and when to layer
- Before you cancel: what to check on your certificate
- Frequently asked questions
What OMA Insurance Actually Includes
OMA Insurance is not one policy. It is an insurance distribution agency owned by the Ontario Medical Association, and it sells several different things, each with its own rules. Before you can decide what to keep or change, you have to know which pieces you actually hold.
Most physicians I review lump it all together as “my OMA insurance.” In practice you are usually dealing with three or four separate programs, with different eligibility, different fine print, and an insurer that is named on each certificate rather than on the OMA logo.
Group life
Term Life Plus 75 and Flex Term Life, issued under an OMA group policy. Coverage built for a defined period, not permanent estate planning.
Group disability
Up to $25,000 a month, with optional riders. The coverage most physicians lean on hardest.
Group critical illness
Up to $250,000 across 25 listed conditions, for you and your spouse. Coverage ends at age 70.
OPIP
OMA’s member bundle of health benefits with a smaller critical illness amount, under its own eligibility rules. For the health and dental side, OMA Insurance is the right contact.
Two things trip people up here. First, the OMA name is not the insurer. OMA says it has moved its insurance program to Manulife, but the insurer that counts is the one named on each of your certificates, and that is who you deal with on a claim or a change. Second, OPIP is its own animal. It covers health benefits plus a smaller critical illness amount, which is a different job than individually owned life or disability coverage. People assume OPIP replaces those. It does not.
One more point worth making, because almost no comparison mentions it: OMA Insurance also sells individually owned products, including permanent life, disability, long-term care, and critical illness, on top of the group plans. So “OMA versus private” is not really the right framing. The honest framing is group coverage versus individually owned coverage, and that distinction matters far more than whose logo is on the certificate.
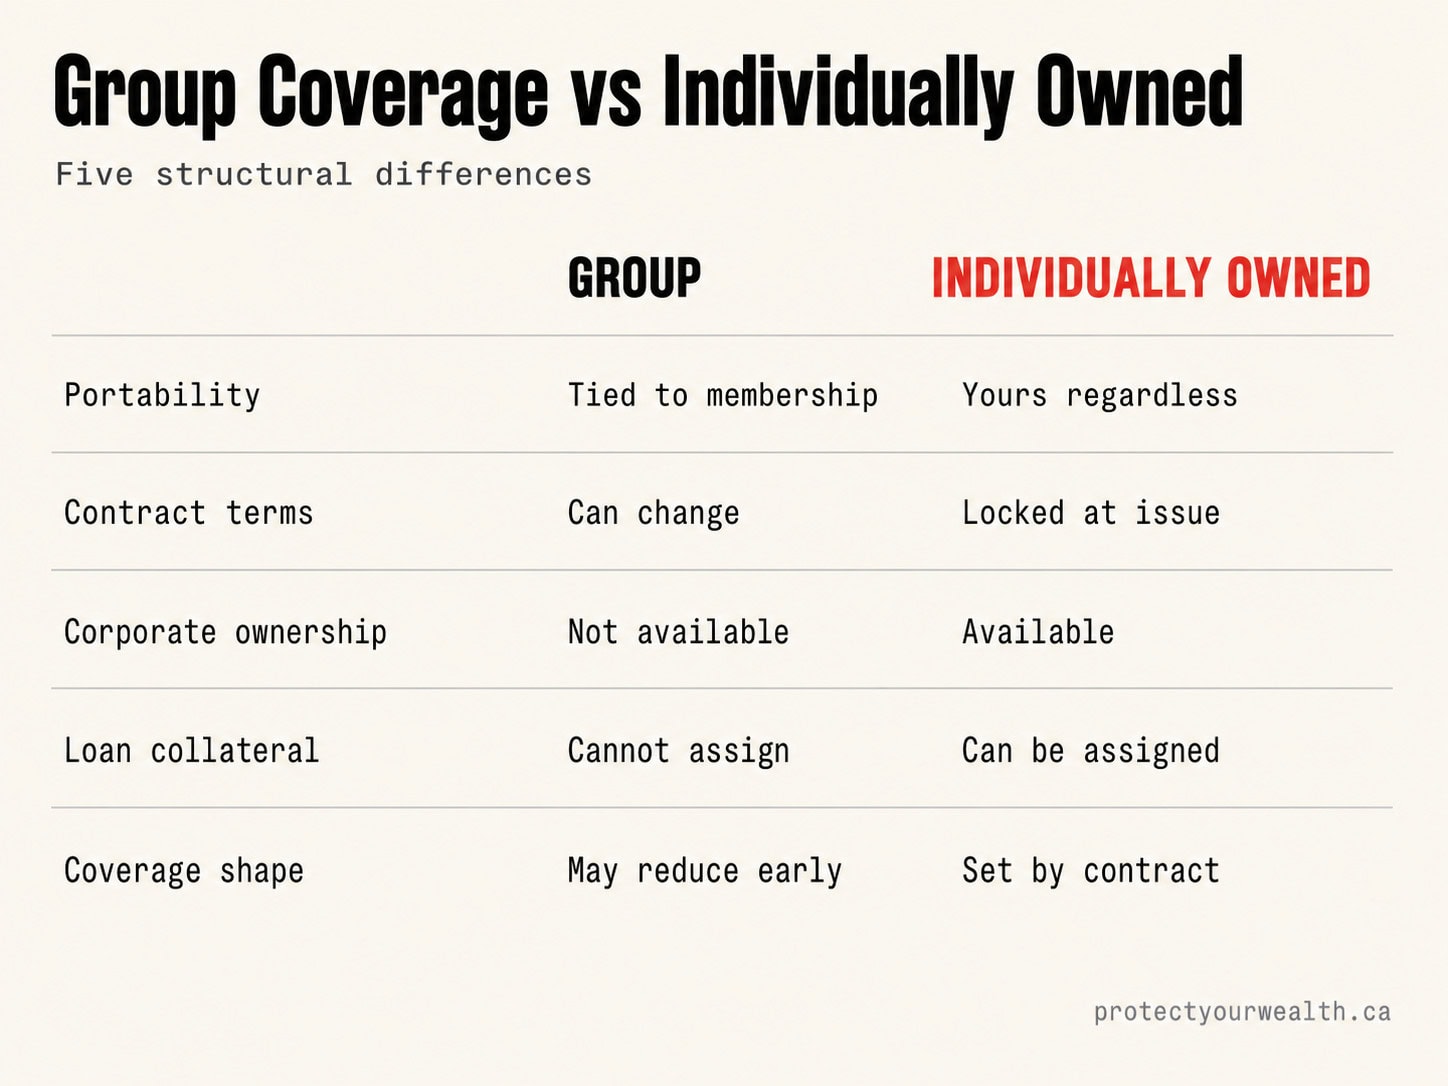
We get into where each one fits in the keep, layer, or replace section below.
If you want the plain-language version of why an individually owned, portable policy behaves so differently from a group certificate, that is worth understanding before you read the rest of this: group versus individual coverage is the whole game.
OMA Life Insurance: Term Life Plus 75 and Flex Term
OMA’s group life insurance works well as a starter layer, but it is built around a defined period, not lifelong protection, and that is the part physicians tend to miss. There are two products, and they behave differently.
| Flex Term Life (10 or 20 year) | Coverage roughly $100,000 to $3,000,000. Rates are level for the first 10 or 20 years depending on the option, then they rise. It can convert before age 65 to a Group Level Term to Age 100 product without new medical evidence, which is useful, but note that is still group term, not individually owned permanent insurance with cash value. |
| Term Life Plus 75 | Personal and spousal coverage up to roughly $1,000,000 each, with higher totals possible by combining other OMA policies. Coverage starts reducing at age 66 and steps down until only about 10% remains at 75, at which point it is paid up. Premium refunds have been paid on this plan in some years, but they are not guaranteed and depend on the plan’s experience, so do not count on one when you compare cost. |
Source note: OMA Insurance plan details on this page (coverage amounts, riders, reduction and termination ages, covered conditions, and refund features) are based on publicly available OMA Insurance plan information. Benefits, eligibility, riders, rates, refunds, and contract terms can change. Confirm the details against your own certificate before making any decision. Protect Your Wealth is not affiliated with the OMA or OMA Insurance.
Here is what physicians actually want to know: how does that compare on price to a policy you own outright? For a healthy non-smoker, individually owned term is often very affordable at the coverage amounts doctors need.
The reason that matters: at those prices, a physician can often own $1,000,000 of term that is locked in and portable for a modest monthly cost, separate from any association membership. You can compare term life quotes for your own age and amount. Whether that replaces your OMA term or layers on top of it depends on your situation, which is the point of the keep, layer, or replace section below.
Group Term vs Individual Term: Where the Costs Cross Over
Group policies seem to be good deals until the numbers are actually dissected further. I have been saying that to physicians for years, and the reason is how association term is usually priced: in age bands, where the premium steps up every few years instead of staying level.
I do not have OMA’s current rate table on this page, so the two examples below are other association plans I ran for clients. They are not OMA rates. They show the pattern to look for when you open your own.
Annual premium by age, $500,000 of coverage
Not OMA rates. A 2018 association plan for a 44-year-old, priced in age bands, against a level-premium term to 65.
■ Group plan ■ Level term to 65
Age 44
$506
$1,034
45 to 49
$862
$1,034
50 to 54
$1,416
$1,034
55 to 59
$2,210
$1,034
60 to 64
$3,432
$1,034
Cheaper in total
Group through 52, level from 53
Total paid by 65
$40,106 group vs $21,722 level
In that example the group plan really was cheaper for the first nine years. From age 53 the level policy pulled ahead, and by 65 the group plan had cost about $18,400 more, nearly twice as much for the same coverage.
A 2026 run on the Alberta Medical Association’s group term plan showed the same shape at $2,500,000 for a 43-year-old non-smoker. Using the plan’s published rates before any premium credits, which are declared each year and not guaranteed, the association plan stayed cheaper in total until about age 57, against an individual 20-year term at the best available rate class.
What decided the $2.5 million comparison
Need ends before about age 57
Group plan cost less in total
Need runs the full 20 years
Individual term 20 was $19,894 cheaper
Standard individual rates, 10 years
Group plan was $383 cheaper
Standard individual rates, 20 years
Individual still about $5,100 cheaper
So a group plan is not automatically the expensive choice. The only other reason to stay the course would be if the remaining term was all that was desired, which is what I told one physician weighing his renewal. The answer turns on how long you need the coverage and which rate class you qualify for, and running this same table on your OMA rates is part of the certificate review further down this page.
The bigger structural issue is that neither OMA product converts to an individually owned permanent policy. So if your reason for holding life insurance is short-to-medium-term family protection while the kids are young and the mortgage is large, OMA term can do that job. If your reason is estate planning, leaving a tax-efficient amount to your family or your corporation decades from now, group term that shrinks after 66 is the wrong tool. That is a job for permanent, cash-value life insurance that you own outright.
This is also group coverage tied to your OMA membership: it stays in force as long as you remain a member and keep paying. An individually owned policy is yours regardless of what association you belong to, and its contract terms are locked in once it is issued, as long as you pay the premiums. For many physicians the right answer is keeping a modest OMA term layer while it is cheap and adding owned coverage for the long-term piece.
One caution before you act on any of this: do not drop an existing life policy until a replacement is approved and in force. Your health today is not guaranteed to be your health at the next application, and that is the one mistake that is hard to undo.
OMA Disability Insurance: What It Covers, and the Gaps That Matter
OMA disability insurance is solid group coverage, but it is not built the same way as a fully individual contract. And on the individual side, physician income protection on a non-cancellable contract has narrowed to two carriers. Here is how I put it when clients ask.
“For physician disability, it really comes down to two companies now, Canada Life and RBC. In my experience that is where most physician cases get compared, because those two compete hard for this segment. Manulife was the third option, but they stopped selling their standalone non-cancellable disability contracts a few years ago. So we look at the two that are left and see what their current promotions are.”
So when you compare OMA’s group disability to private, you are realistically comparing it to a Canada Life or RBC individual contract. OMA’s plan covers up to $25,000 a month, and it is genuinely useful coverage. But there are differences that matter once your income is real.
Price is usually the first one physicians notice, because the group plan often looks cheaper in year one. Individual policies typically cost more upfront because the insurer prices in long-term risk on day one, rather than deferring it into future premium increases. Put simply, group disability prioritizes lower initial cost, and individual disability prioritizes long-term certainty.
Start with what OMA actually gives you, because the old story that it has no recovery benefit is not accurate. The current plan includes total and residual disability, a survivor benefit paid to your estate, an optional cost-of-living rider, a guaranteed insurability rider so you can increase coverage after residency without new medical evidence, and even a retirement protection rider that keeps funding a savings account while you are disabled. That is a fair package.
The own-occupation question is where physicians get tripped up. Here is the part that actually matters:
“The regular occupation rider is imperative, especially as a physician. If you’re not able to work as a doctor but you’re able to work as a Walmart greeter, without that rider the insurer can say you’re able to work and your coverage doesn’t pay. We want you covered if you can’t work in your own profession, regardless of what else you could theoretically do.”
Two clarifications on that. Insurers label this protection differently, own occupation or regular occupation, and the exact wording varies by contract. And an any-occupation test usually looks at work you are reasonably suited for by education, training and experience, not literally any job. For a specialist who can no longer practise, that can still mean benefits stop while a non-clinical role is available, which is why the rider matters.
OMA does offer an Own Occupation rider, and a practising physician can add it. The catch is that the true own-occupation definition is generally not available to residents, medical students, or international medical graduates under the OMA plan, and the base definition can be narrower than the specialty-specific definition you would build into an individual contract. So “I have OMA disability” does not automatically mean “I have own-occupation coverage for my specialty.” Confirm what is actually on your certificate. That one detail can materially affect how a claim is assessed and whether benefits continue if you can work in another occupation.
None of this means cancel OMA. It means know exactly what you hold, then decide whether to layer an individual policy over it or replace it. If you want to see how the individual carriers stack up, start with our look at the top disability insurance companies in Canada, and when you are ready to compare actual contracts we can pull disability insurance quotes from the carriers that specialize in physicians.
This is exactly the point where a second set of eyes on your certificate pays for itself. Most physicians I sit down with have never read the definition of disability in their own plan. Book the free certificate review and we will read it together before you change anything.
OMA Critical Illness and OPIP Critical Illness
OMA gives you critical illness coverage in two separate places, and most physicians do not realize they are two different things. There is the standalone group CI plan, and there is the smaller CI benefit built into OPIP. Both are group coverage tied to your OMA membership, and neither works like a policy you own.
$250K
Max standalone CI benefit, subject to underwriting
25
Covered conditions
Age 70
Coverage ends
2 lives
Member and spouse can both be covered
The standalone plan pays a tax-free lump sum, up to $250,000, if you are diagnosed with one of 25 covered conditions and survive the required period. The money is yours to use however you need: out-of-country treatment, time off, paying down the practice loan, replacing a spouse’s lost income. That is real, useful coverage. Just know the ceiling is $250,000 and the coverage stops at 70.
OPIP is the other piece. It is OMA’s member bundle of health benefits with a smaller critical illness amount built in, and it is genuinely good value for what it is. The mistake is treating that smaller amount as your critical illness plan. For a physician with a mortgage, a corporation, and dependents, it is a layer, not the whole answer. For OPIP’s health and dental benefits themselves, OMA Insurance is the right contact; that is not something we advise on.
Where individual critical illness pulls ahead is on size and shape. Individual CI can be written for much larger amounts, subject to underwriting and income: Manulife’s Lifecheque, for example, publishes a $2 million maximum, and Desjardins will go to $4 million on request. Individual plans can also run past age 70, to age 75 or to 100, and some include features OMA’s group plan does not, such as return-of-premium riders or a built-in benefit for loss of independence. Whether any of that is worth the cost depends entirely on your situation, and I would not assume bigger is automatically better. It depends what problem you are solving.
If you are weighing whether critical illness belongs in your plan at all, start with whether critical illness insurance is right for you. When you want to see what individually owned coverage would actually cost against your OMA amount, we can pull critical illness insurance quotes and compare them side by side.
Owning Insurance Through Your Medical Professional Corporation
If you are incorporated, the single biggest planning question is not which policy to buy, it is who should own it: you personally, or your medical professional corporation. OMA’s group plan cannot answer that question, because group coverage cannot be owned by your corporation. An individual policy outside the group plan can generally be owned either way, personally or by your corporation, subject to the insurer’s ownership rules. That alone is often the reason an incorporated physician looks past the association plan.
Here is the context most doctors were never told:
“The government, about twenty years ago, allowed physicians and dentists to set up professional corporations. Previously there was no ability to do this. It was part of a negotiation, instead of raising physician fees, they created this tax shelter. That’s its origin. And it’s become one of the most powerful wealth tools available to incorporated professionals.”
That same corporation can own life insurance. When it does, two things change. The premiums are paid with corporate dollars, which for many physicians have been taxed at a lower rate than personal income before they ever leave the corporation. And on death, the death benefit can flow into the corporation, and a large part of it can be credited to something called the capital dividend account.

What the capital dividend account does, in plain terms
The capital dividend account, or CDA, is a notional balance inside your corporation. When a corporate-owned policy pays a death benefit, the amount above the policy’s adjusted cost basis credits the CDA. Money paid out of the CDA can generally reach your shareholders or your estate without the usual tax that a regular dividend would carry. In practice, that can mean the difference between your family receiving the full value of the insurance and receiving it after a meaningful tax hit. The exact numbers depend entirely on the policy and your corporate structure, so this is a conversation for your accountant and the actual illustration, not a rule of thumb.
This is where it stops being a product comparison and starts being planning. A few of the ways incorporated physicians use corporately owned coverage:
- Estate liquidity. Permanent insurance owned by the corporation creates a tax-efficient pool to cover the tax bill that lands at death, so the family is not forced to sell assets or wind down the practice in a hurry.
- Tax-sheltered growth. Passive investment income earned inside a corporation is taxed at high rates, and once it passes $50,000 a year it starts to reduce the federal small business deduction on your active income. Certain permanent policies let the corporation hold value inside the policy in a tax-advantaged way instead. This is a job for permanent life insurance, not term.
- Partnership and buy-sell needs. If you practise in a group or own a clinic with partners, corporately owned coverage can fund a buy-sell agreement so a surviving partner can buy out a deceased partner’s share cleanly.
I want to be careful here, because this is exactly the area where bad advice does damage. Corporately owned insurance is not automatically better than personally owned. It depends on your income, your corporate structure, whether you actually have retained earnings to fund it, and what your accountant is already doing with the corporation. I have seen physicians put insurance in the corporation when personal ownership was the cleaner answer, and the reverse. The right structure is a decision made with your accountant, with the policy illustration in front of both of you.
Make that decision before the policy is issued, not after. On one recent file, a physician’s new policy was already in force in his own name when he decided his corporation should own it. The insurer treated the change as a full reissue, with replacement paperwork signed by him and by me, and it took about three months to finish.
What I can tell you plainly is that OMA’s group plan takes this entire option off the table. If you are incorporated and that matters to your planning, that is not a small footnote. It is one of the main reasons to look at individual coverage, and it is worth mapping out with your accountant before you commit either way.
Using Life Insurance as Collateral for a Practice Loan
When you borrow to buy into a practice, open a clinic, or finance equipment, the lender will often want life insurance as security on the loan, and that insurance can be structured so it does double duty. This is called a collateral assignment, and it is something a group plan like OMA’s generally cannot do.
The mechanics are simpler than they sound. You own a life insurance policy. You sign a collateral assignment that names the lender as the party entitled to be paid first, up to the outstanding loan balance, if you die while the loan is still owing. The bank gets its security. Your family or estate keeps whatever is left over above the loan. When the loan is paid off, the assignment is released and the policy is fully yours again.
Why bother doing it this way instead of letting the bank sell you its own creditor insurance on the loan? Because you control the policy, not the bank. Creditor coverage on a business loan is typically owned by the lender, shrinks as your loan balance drops, and disappears when the loan is gone. A policy you own stays level, stays with you after the loan is paid, and can keep doing other jobs in your plan. It is the same argument that runs through this whole page: owned and portable beats tied to a product you do not control.
There is also a tax angle worth raising, carefully. When a lender requires the insurance as a condition of the loan and the policy is collateral-assigned to that lender, a portion of the premium may be deductible to the business under the Income Tax Act. The conditions are specific and it is not automatic, so this is a question for your accountant and your lender, not something to assume. I am a licensed insurance broker, not a tax advisor, and I would never want you to bank on a deduction without your accountant confirming it for your situation.
The practical point: if a practice acquisition or expansion loan is on your horizon, the time to think about the insurance is before the bank hands you their form, not after. The right amount, the right owner (you or your corporation), and the right structure are easier to set up cleanly at the start. If you also want the loan and your income protected while you are alive, that is where disability coverage and overhead protection come into the same conversation.
If you are financing a practice, structure the insurance alongside the loan rather than after it, so the lender is satisfied and you are not overpaying or over-insured.
When OMA Fits, When Private Fits, and When to Layer
There is no single answer to whether you should keep OMA or go private, and anyone who gives you one without seeing your situation is selling, not advising. In my experience, most physicians end up doing some of each: keep what works, layer private coverage over the gaps, replace only what genuinely underperforms.
This is the principle I hold to, and it is the opposite of how a lot of these comparisons are written:
I never automatically recommend replacing existing coverage, especially after a health change. The first job is to protect what you already have. Then we look at what to add. Cancelling something that is already in force, before a replacement is approved, is how people end up uninsured at the worst possible moment.
Sometimes the right answer is less coverage, not more. A later-career physician came to me holding OMA coverage, a second association plan and workplace plans, while another plan’s representative was urging a switch. This was not a question of a new plan at all; it was which coverage to keep and which to reduce. As I put it on that call, “you don’t need more. You need less.” I look at which plan gives you coverage longest at the best premium, and I keep in mind that an association plan’s representative represents that plan.
So instead of a winner-takes-all table, here is how I actually think about it by situation:
When OMA often fits
- You are a resident, student, or new physician and want coverage in place now, cheaply
- You need a starter layer while income and plans are still settling
- You have a health history that could make individual underwriting harder, and existing OMA coverage is valuable to hold
- OPIP’s health and CI benefits genuinely suit you
- You are later in your career and the real job is trimming overlapping plans, not adding new ones
When private deserves a close look
- You are incorporated and ownership, CDA, or estate planning is in play
- You are a procedural specialist who needs stronger own-occupation wording
- You want contract guarantees that cannot be changed on a group basis
- You need coverage past age 70, or higher limits than the group plan allows
- You are financing a practice and want a policy you can collateral-assign
When layering is the smart play
- Keep a modest OMA term layer while it is inexpensive
- Add owned permanent or long-term coverage for the estate piece
- Hold OPIP for health benefits, add private CI for the larger amount
- Keep group DI in residency, move to an owned contract as income grows
Notice that “replace everything” is not its own column. That is deliberate. Wholesale replacement is rarely the right answer, and it carries real risk: if your health has changed since you first got covered, a new application can come back rated, excluded, or declined, and now you have given up coverage you cannot easily get back. The same logic applies whether we are talking about an association plan, a group versus individual decision, or coverage you hold as part of a couple, which has its own wrinkles worth reading in our guide for couples.
The work, the part that actually protects you, is reading your current certificate, identifying the real gaps, and only then deciding what to add, reduce or change. That is a free conversation, and it is the whole reason this page exists.
Before You Cancel OMA: What to Check on Your Certificate
Do not cancel a thing until you have read your own certificate and a replacement is approved and in force. That one rule prevents the worst outcome in this entire process: dropping coverage you already have, then finding out at the new application that your health has changed and you no longer qualify the way you used to.
In my experience, most physicians have never actually read their OMA certificate. They know roughly what they pay and roughly what they are covered for, and that is it. Before you change anything, here is what to pull out of the document and have in front of you.
Have these on hand before any decision
- The exact coverage amount on each product: life, disability, critical illness
- The insurer named on each certificate
- Your disability definition, and specifically whether the Own Occupation rider is on your certificate
- Premium type: step or level, and what triggers an increase
- Termination ages: when each coverage ends or reduces (life reduces from 66, DI and CI end at 70)
- Any riders you are paying for: cost-of-living, guaranteed insurability, retirement protection
- Whether any amount was issued without medical evidence, which can carry a pre-existing limitation
- What you are paying in OMA membership dues to keep the coverage active
With that in hand, the decision gets simple. You are not guessing anymore. You can see exactly where the gaps are, whether the own-occupation wording protects your specialty, what ends at 70 that you might want to run longer, and whether the corporate or practice-loan angles from earlier on this page apply to you. Then, and only then, do you look at what to add or replace.
If the new coverage replaces an individual policy you already own, Ontario adds a safeguard. Your advisor has to give you a replacement declaration and a written explanation of the advantages and disadvantages of replacing, review both with you, and have you sign them, and you can still withdraw the new application within 20 days of receiving them. I also keep the old coverage in force until the new policy is issued, because I would want the paperwork issued on it.
This is the part where a second set of eyes earns its keep. Bring your certificate, or your insurer’s summary for your disability and critical illness coverage, and we will read it together, line by line, and tell you plainly what is worth keeping and what is not. No pressure to switch, and nothing gets cancelled until something better is actually in place. How to book that review is just below the FAQ.
Frequently Asked Questions
QUESTION 01
Who actually underwrites OMA insurance?
Check your certificate, because the insurer is named there, not on the OMA logo. OMA Insurance is a distribution agency owned by the Ontario Medical Association, and OMA says it has moved its insurance program to Manulife. The insurer named on each benefit is who you deal with for a claim or a change, so confirm it line by line before you call.
QUESTION 02
Is OPIP the same as OMA critical illness insurance?
No. OPIP is OMA’s member bundle of health benefits with a smaller critical illness amount built in. OMA’s standalone group critical illness plan is separate and covers up to $250,000. Many physicians hold both and assume the OPIP amount is their full critical illness coverage, when it is really a starter layer. For OPIP’s health and dental benefits, OMA Insurance is the right contact.
QUESTION 03
Does OMA disability insurance include own-occupation coverage?
OMA offers an Own Occupation rider, and a practising physician can add it. The catch is that the true own-occupation definition is generally not available to residents, students, or international medical graduates under the OMA plan, and the base definition can be narrower than the specialty-specific wording you can build into an individual contract. Always confirm what is actually printed on your certificate, because that one detail can materially affect how a claim is assessed and whether benefits continue if you can work in another occupation.
QUESTION 04
Can I own OMA coverage through my medical professional corporation?
No. OMA’s group coverage cannot be owned by your corporation. If corporate ownership matters to your planning, for capital dividend account purposes or estate liquidity, you need an individual policy outside the group plan, owned by your corporation. Whether corporate or personal ownership is right for you is a decision to make with your accountant.
QUESTION 05
Should I cancel my OMA coverage if I can get private insurance?
Not until a replacement policy is approved, issued, and in force. Cancelling existing coverage first is the most common and most damaging mistake, because if your health has changed since you were first covered, a new application can come back rated, excluded, or declined. The safe sequence is always: review, apply, get approved, then decide what to keep or drop.
QUESTION 06
Is OMA insurance mandatory if I am an OMA member?
No. Being an OMA member does not require you to buy your insurance through OMA. You are free to shop the open market, and most physicians benefit from comparing their OMA coverage against individually owned options before deciding what to keep, layer, or replace.





